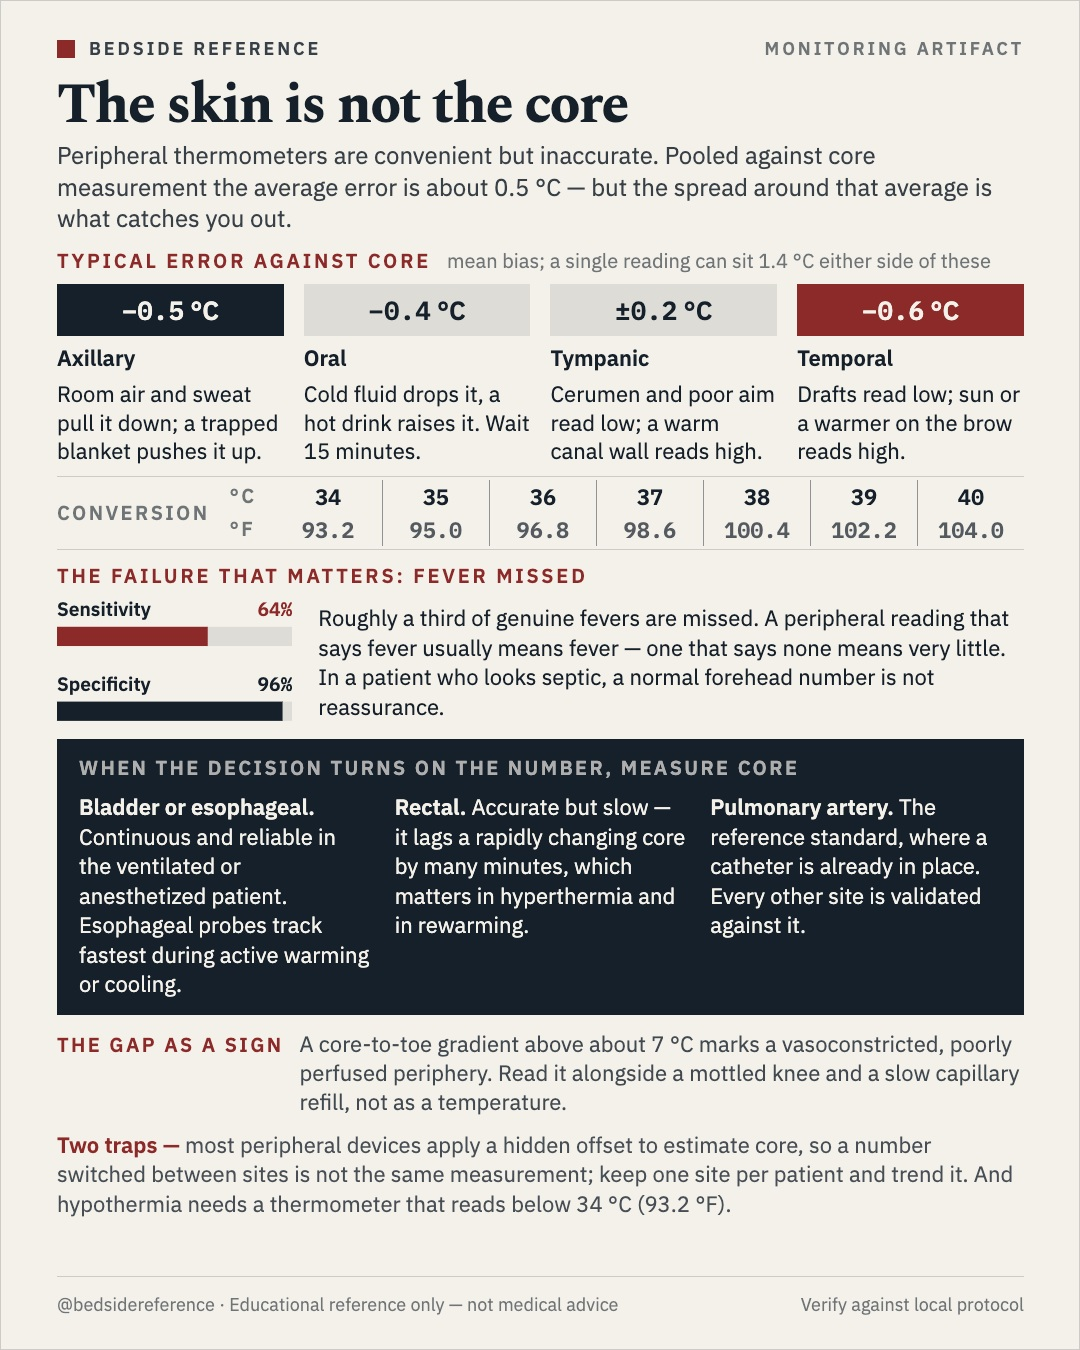
The skin is not the core.
Peripheral thermometers miss about a third of real fevers. A forehead reading that says no fever means very little — when the decision turns on it, measure core.
Reviewed September 2026 · verify against current guidelines
The skin is not the core.
Peripheral thermometers are convenient but inaccurate. Pooled against core measurement the average error is about 0.5 °C — but the spread around that average is what catches you out.
Typical error against core — mean bias; a single reading can sit 1.4 °C either side of these
| Site | Bias | What moves it |
|---|---|---|
| Axillary | −0.5 °C | Room air and sweat pull it down; a trapped blanket pushes it up. |
| Oral | −0.4 °C | Cold fluid drops it, a hot drink raises it. Wait 15 minutes. |
| Tympanic | ±0.2 °C | Cerumen and poor aim read low; a warm canal wall reads high. |
| Temporal | −0.6 °C | Drafts read low; sun or a warmer on the brow reads high. |
Conversion
| °C | 34 | 35 | 36 | 37 | 38 | 39 | 40 |
|---|---|---|---|---|---|---|---|
| °F | 93.2 | 95.0 | 96.8 | 98.6 | 100.4 | 102.2 | 104.0 |
The failure that matters: fever missed
Sensitivity 64% · Specificity 96%. Roughly a third of genuine fevers are missed. A peripheral reading that says fever usually means fever — one that says none means very little. In a patient who looks septic, a normal forehead number is not reassurance.
When the decision turns on the number, measure core
- Bladder or esophageal. Continuous and reliable in the ventilated or anesthetized patient. Esophageal probes track fastest during active warming or cooling.
- Rectal. Accurate but slow — it lags a rapidly changing core by many minutes, which matters in hyperthermia and in rewarming.
- Pulmonary artery. The reference standard, where a catheter is already in place. Every other site is validated against it.
The gap as a sign
A core-to-toe gradient above about 7 °C marks a vasoconstricted, poorly perfused periphery. Read it alongside a mottled knee and a slow capillary refill, not as a temperature.
Educational reference only — verify against local protocol.
Sources
Verify against current guidelines and local protocol before acting.
- Niven DJ, et al. Accuracy of Peripheral Thermometers for Estimating Temperature: A Systematic Review and Meta-analysis. Ann Intern Med 2015;163:768–777.
- Lefrant JY, et al. Temperature measurement in intensive care patients: comparison of urinary bladder, oesophageal, rectal, axillary, and inguinal methods versus pulmonary artery core method. Intensive Care Med 2003.
- O'Grady NP, et al. Guidelines for evaluation of new fever in critically ill adult patients. Crit Care Med 2008.
- Joly HR, Weil MH. Temperature of the great toe as an indication of the severity of shock. Circulation 1969.
Downloads
Every card behind this topic, as published — view full size or download.